

A long note can still hide why you made a decision. What a later reader needs from NP documentation, from refusals to addenda to billing.
Last updated: October 2026
I was precepting an NP resident whose patient's kidney function had worsened. Several medications had to stop or change, and we spent most of the visit working through each one and explaining every change to the patient.
Her clinical work was right. When I read her note a few days later, it listed which medications were stopped and which were changed. It did not say why, or whether the patient understood.
Good NP documentation answers one question for anyone who reads the note later: what did you decide, and why? The resident's note recorded what she did and left out why. That gap has nothing to do with length, and it matters at every point where someone depends on the record: when a patient declines the plan, when she goes home with instructions, when new information arrives, and when the visit is billed.
What does someone reading your note later actually need?
They need to know what you decided and why. The NP covering your inbox, a specialist reading your referral, a coder, a quality reviewer, and you yourself in 6 months all arrive at the note with that same question. None of them watched you think. If the reasoning is not written down, a sound decision reads like an unexplained one.
For anyone who was not there, the note is the visit. It is the only account of what you saw, what you weighed, and what you chose.
That includes you. In 6 months you will open this note before her next visit, with hundreds of other patients in between, and you will have only what you wrote.
A note records what you did. A later reader needs to know why.
Why doesn't a longer note show more reasoning?
Length and reasoning are different things. When the reasoning is missing, the instinct is to write more, so notes fill with copied history, auto-filled exams, and paragraphs nobody needed. None of that answers the question a later reader brings. One sentence connecting your finding to your plan answers it.
The NP resident's note was not short. It was complete about everything except the decision.
The Lie of Perfectionism covers why the longer note costs you time without making the record better.
One test helps. Before you close a chart, ask whether someone who was not in the room could read it 2 years from now and see your reasoning. If not, the note usually needs one more sentence, not another paragraph.
More words do not add up to more reasoning.
What should NP documentation show when a patient declines part of the plan?
It should show the decisions that followed, not only the refusal. When a patient declines a referral, a test, or a medication, the plan changes and your reasoning changes with it. A note that reads "patient refused" records the refusal and nothing about what was explained, what else was offered, or what she chose instead.
Take an invented patient who declines a specialist referral. A note that reads "declined referral" does not say whether the reason was explained, whether anything else was offered, or whether the door was left open. The visit may have covered all of it. The note does not show it.
Declining one recommendation is also not declining the rest of the visit. Doing what you can within your setting is not abandoning the recommendation she turned down, and both decisions belong in the record.
The AMA Code of Medical Ethics, Opinion 2.1.1 on informed consent, says the options discussed with a patient should include forgoing treatment, and that the conversation and the patient's decision should be documented in the record. How you structure that depends on your setting and your organization's policies.
A refusal is a decision point, not the end of the note.
How does patient education fit into documentation?
Patient education is the part of the plan the patient carries home, so the record should show what she was told and what she understood. "Patient counseled" says a conversation happened. It does not say what was covered or whether she could explain the plan back, which is what the next person caring for her needs.
Confirming understanding is an established clinical practice. A 2020 systematic review in PLOS ONE by Talevski and colleagues found teach-back (asking patients to explain the plan in their own words) effective in 19 of the 20 studies it reviewed, in settings that included primary care practices and outpatient clinics.
The NP resident's patient went home with several medication changes, and the note should have shown what she was told about each one.
It also matters to whoever answers her next call. If she phones the nurse line next week, the person on the other end needs to know what she was already told, so the advice she hears matches yours.
"Patient counseled" records that you talked, not what she heard.
What do you do when your reasoning changes after the visit?
You add to the record without erasing what is already there. A consult report or result arrives, or the patient remembers something on the phone, and your thinking changes. An addendum records that change with its own date, time, reason, and signature. Altering the original entry hides what you knew at the time.
That is the standard in the American Health Information Management Association's 2012 toolkit on amendments in the electronic health record, which says the original documentation should stay intact alongside the change.
The NP resident did exactly this. She added an addendum with the reason for each change and what the patient understood, and the record was complete.
An addendum is not an admission of failure. It shows an NP who kept following the patient after the visit ended. Follow your organization's policy on late entries, and ask your health information team when it is unclear.
Add to the record. Never rewrite it.
Why does the same reasoning decide how a visit is billed?
The person who sets the visit level is looking for the same reasoning. Since January 2021, office visit levels have been set by medical decision making or by total time. Decision making rests on 3 elements: problems addressed, data reviewed, and risk of the plan. A note that does not show them cannot support the level earned.
Those rules come from the American Medical Association's CPT guidelines for office and outpatient visits, as described in the AMA's current E/M FAQ. Coding rules change, so verify the details at the source and with your organization's coding team.
The NP resident's visit was complex, but her first note showed the changes and not the thinking, so it did not show the complexity either.
Under-documenting cuts both ways. A note that hides complexity gets billed below the work it took, a note billed above what it shows can be taken back in an audit, and a note that is not signed cannot be billed at all. Prior Authorization Documentation That Gets Approved the First Time covers the same principle for prior authorization reviewers.
The reasoning that helps the next reader is the same reasoning that supports the bill.
What does the gap look like in a real note?
The gap is the space between what a note records and what a later reader needs to act on. Each common shortcut below records that something happened and leaves out the decision behind it. The last column describes what a complete record lets a reader see, not the wording, because the wording should be yours.
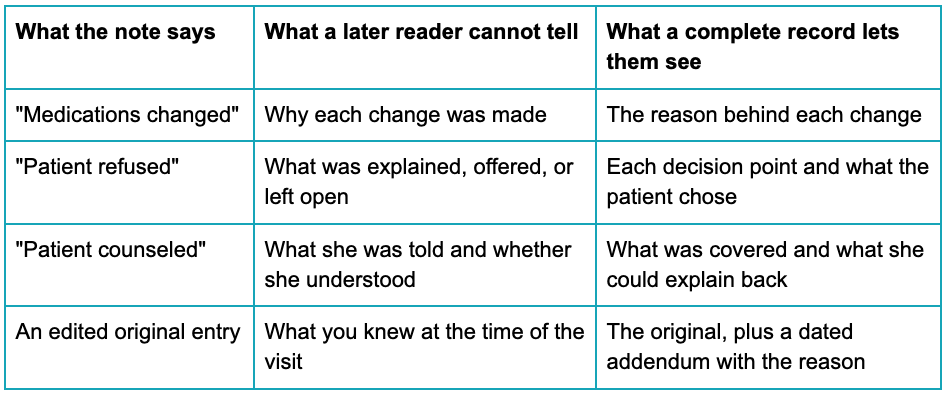
Every shortcut records the event and drops the decision.
How do you capture the reasoning without adding time?
Write it in the room, while the decision is still in front of you. Reasoning written at 9 PM is reconstructed from memory and takes longer. Reasoning written during the visit takes one sentence, because you explained it out loud to the patient minutes earlier. The NP resident had already said every reason aloud; it never reached the page.
I talk about why decisions get lost between the room and the note in Why NPs Forget What They Decided.
A note structure helps when it makes the sentence connecting your finding to your plan the obvious next thing to write, without making the note longer.

Give the reasoning a place in every note
If your notes start from a blank page, the reasoning is the first thing to get squeezed out. The SOAP Note Template and User Guide is a free starting structure that leaves room for your reasoning at each step, without lengthening the note.
The visits where the reasoning changes most often are the ones that come back every few months: a blood pressure still not at goal, a medication adjusted again, a plan that shifted for a reason the next reader needs to see.

For the chronic disease visits on your schedule every week
The Chronic Disease Chart Smart Kit Bundle gives you ready-to-save documentation for 7 common chronic conditions, built so the assessment and plan show what you considered and why. You save it once in your own EHR and reword it in your own voice.
Frequently asked questions
Do I need to document every conversation with a patient?
No. Document the conversations that changed or explain a decision: why the plan is what it is, what the patient was told to act on, and what she chose when she declined something. A later reader does not need a transcript. They need enough to follow your reasoning and continue the care without calling you.
Is it okay to add an addendum days after the visit?
Yes, when new information arrives or something important was missing. AHIMA's 2012 toolkit on EHR amendments describes an addendum as carrying its own date, time, reason, and signature, with the original entry left intact. Follow your organization's policy on late entries, and never edit the original to make it look complete.
Does documenting reasoning make notes longer?
Usually not. The reasoning is often one sentence that connects a finding to a decision. Notes get longer when the reasoning is missing and the gap is filled with copied history, auto-filled exam text, and general counseling language. A note built around the decision tends to be shorter and easier for the next reader to use.
Should NPs write notes defensively?
Write for the next person who has to act on the note: the covering NP, the specialist, the coder, and yourself later. A note that shows what you decided and why serves every one of them. Notes written to anticipate an argument tend to grow long and vague, which makes the reasoning harder to find, not easier.
The sentence that was missing
Good NP documentation records what you decided and why, wherever someone else depends on the note. Capturing it in the room keeps it from costing extra time.
The NP resident's clinical work was right the first time. What she added later was not more work. It was the sentence that let everyone else see the work she had already done.
Your chart is the record. Make sure it shows your thinking.
Related Reading
The Lie of the Default EHR: Why You Still Have Work After the Visit: why the EHR you were handed slows you down until you tailor it to how you think.
The Lie of Perfectionism: why a longer note costs you time without making the record better.
Prior Authorization Documentation That Gets Approved the First Time: what a reviewer needs to see before approving a request.
Candice Elam, DNP, FNP-C, is a family nurse practitioner who practices full-time at an FQHC in New York City and precepts NP residents and students. She founded SignTheChart to help NPs finish their work inside their scheduled business hours.
